


In this article
Chronic neck pain, TMJ clicking, and tension headaches often share one source. The jaw and cervical spine are governed by overlapping muscles, shared fascia, and converging nerve pathways.
Research has documented this connection at a level most clinical practice still treats as separate. A study in BioMed Research International found a correlation of 0.915 between jaw disability and neck disability, one of the highest correlations recorded between two regions of the body that are usually treated independently.
This guide walks through the jaw and neck anatomy: which muscles share the load, how fascia carries tension between regions, the nerve pathway that processes both as one, and what happens when the connection goes unaddressed.
The short version
Your jaw and neck share muscles, one continuous layer of fascia, and a single nerve processing hub in the brainstem. That is why jaw tension, neck stiffness, and tension headaches so often travel together, and why treating one region on its own rarely holds.
The muscles that connect your jaw to your neck
Most people think of the jaw and neck as separate regions. Anatomically, they are not.
The masseter, the main chewing muscle you can feel tighten when you clench, runs from your cheekbone down to your lower jaw. It shares fascial tissue with the sternocleidomastoid, the large muscle running down both sides of your neck. When the masseter is chronically tense, that tension does not stay contained. It travels. A jaw that feels tight, or a tightness you notice on one side when you wake, is usually the first place this shows up.
Below the jaw, the digastric muscle connects the chin to the hyoid bone, a small bone in your throat that acts as a mechanical anchor for both the tongue and the neck muscles below it. The hyoid has no direct joint to the spine. It is held entirely by muscle and fascia. When jaw tension pulls the hyoid forward or down, the muscles attaching to it, which connect to the cervical vertebrae, shift their resting position to compensate.
The upper trapezius and temporalis muscles show the same pattern: high tenderness in these muscles goes with high levels of both jaw and neck dysfunction. These are not adjacent problems. They are the same problem expressed through a connected system.
Go deeper: how to release jaw tension and calm the neck with it (free e-book inside with the Posturepro+ subscription).
How fascia carries tension from jaw to spine
Muscle is only part of the story. Surrounding every muscle in your jaw and neck is a continuous layer of connective tissue called fascia. Unlike muscle, fascia does not switch off. It transmits force continuously, meaning tension in one area is felt throughout the connected chain.
The deep cervical fascia wraps the muscles of the neck and continues upward, connecting directly into the fascial layers of the jaw and face. The stylomandibular ligament, which anchors the lower jaw, is anatomically described as a thickening of this same deep cervical fascia. The jaw and the neck are not just close to each other. They are wrapped in the same continuous sheet of connective tissue.
Why TMJ pain travels
This is why TMJ dysfunction so frequently produces pain not just in the jaw, but in the temples, behind the eyes, at the base of the skull, and into the shoulders. The fascia does not recognize regional boundaries. It carries load wherever the connected chain leads.
Research on the masticatory muscles confirms this: the jaw muscles and their fasciae are considered part of the same craniocervical unit as the cervical muscles. Treating either side without accounting for the other leaves half the system unaddressed.
The nerve pathway behind it
Beyond muscle and fascia, the jaw and neck are connected by something even harder to treat locally: a shared nerve pathway.
The trigeminal nerve carries sensation from the entire face and jaw: pain, pressure, position. It is the largest of the cranial nerves. What most people are not told is where that nerve terminates. It feeds into a region of the brainstem that extends down into the upper cervical spinal cord, the same area that processes sensation and position from the neck.
Pain messages from the jaw and pain messages from the neck arrive at the same processing hub. Research confirms that the more severe the TMJ dysfunction, the greater the cervical dysfunction observed: a dose-response relationship that only makes sense if both are driven by the same underlying system.
The clinical evidence for this is direct. A clinical trial found that treating only the cervical spine, without touching the jaw at all, produced measurable improvements in TMJ function. And treating only the TMJ produced significant improvements in cervical range of motion and reduction of spinal pain. The two regions are not separate. They share one regulatory system.
One system, studied as one
Because the jaw and neck share muscles, fascia, and a nerve pathway, it makes sense to learn them together. The Jaw and Body Connection course does exactly that: it follows the jaw into the neck, spine, and nervous system, and shows you how to check for a jaw imbalance yourself.
What happens to jaw and neck posture when this goes unaddressed
In the short term, the pattern is manageable. Neck stiffness that loosens up by midday. A jaw that clicks when you eat but does not hurt. Headaches every few weeks, not every day. The body is compensating, and it can compensate for a long time, until the compensation itself becomes the problem.
As the jaw and neck adapt to each other's dysfunction, the muscles involved develop what researchers call trigger points: areas of chronic tightness that refer pain to other regions. Studies show that people with chronic neck pain have significantly more latent trigger points in the jaw muscles than healthy controls, even when they report no jaw pain at all. The jaw is involved. It just has not started hurting yet.
Over time, the chain extends downstream. Cervical compensation drives upper-back compensation, which drives hip and pelvic compensation, which changes how weight loads through the foot. The jaw is not just connected to the neck. It is one of the sources of information the brain uses to organize posture through the whole body.
Correcting Both Ends of the Chain
The jaw and neck are part of a postural chain that runs through the spine to the feet. Correcting one end of that chain still leaves the other end alone, which is why a jaw or neck pattern so often returns after treatment that addressed only one region.
Jaw and Body Connection
Discover How Your Jaw Influences Your Posture, Balance, and Movement.
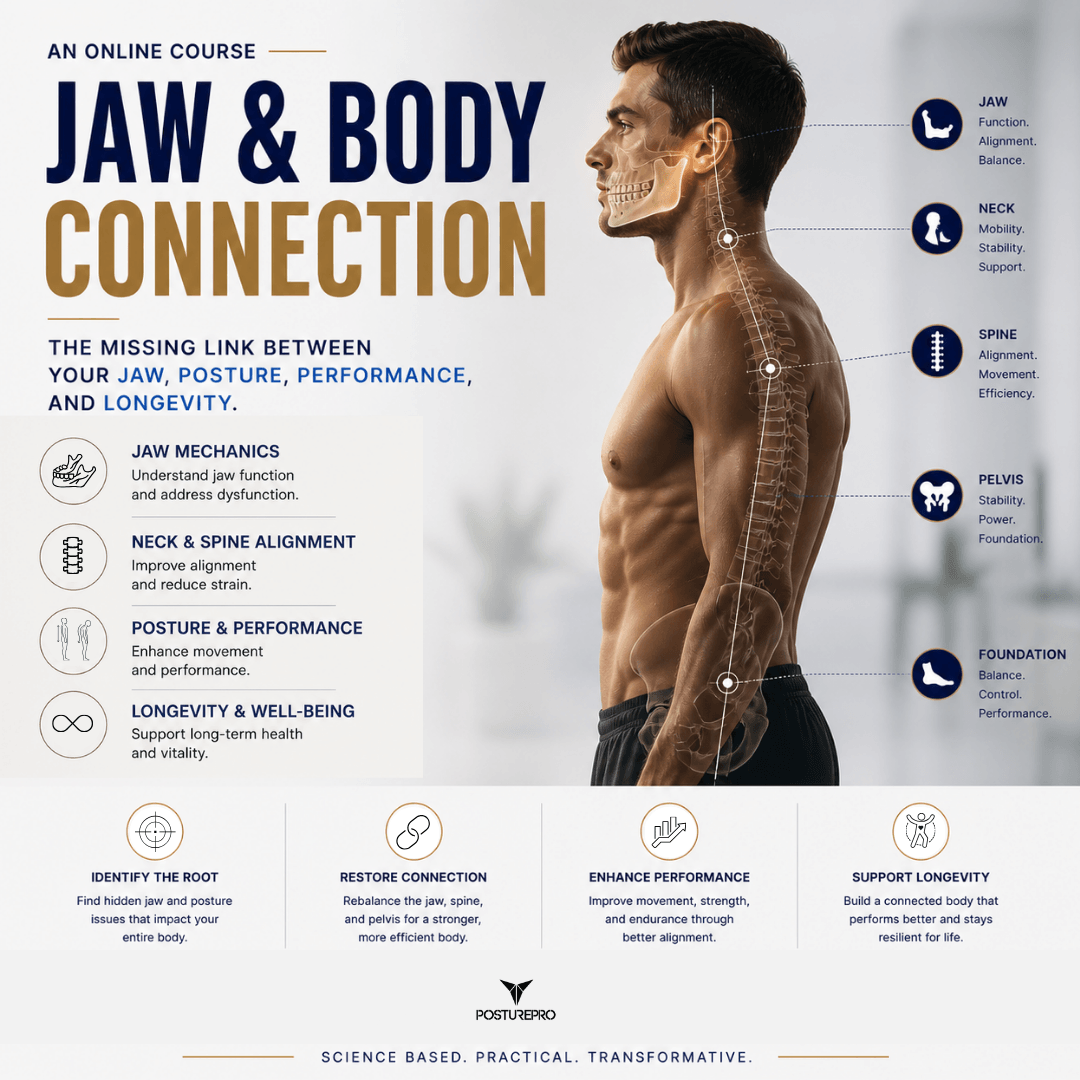
- ✓ Understand how jaw position, tongue function, and muscle tension can influence posture and body alignment.
- ✓ Explore the neurological connections between your jaw, neck, spine, and nervous system.
- ✓ Learn practical assessments and techniques to identify jaw imbalances and understand their influence on the rest of your body.
Frequently Asked Questions
Can jaw problems cause neck pain?
Yes. People with TMJ disorders show significantly higher rates of cervical dysfunction and reduced cervical range of motion. The muscles that move the jaw share fascial connections with the muscles that stabilize the neck, which is why tension in one region directly affects the other.
Which muscles connect the jaw and neck?
Three links stand out. The masseter, your main chewing muscle, shares fascial tissue with the sternocleidomastoid that runs down each side of the neck. The digastric runs from the chin to the hyoid bone, which is held in place only by muscle and fascia. And the temporalis and upper trapezius go together: tenderness in both is linked with higher levels of jaw and neck dysfunction.
Why do my chin and neck feel connected?
Because they are. The digastric muscle runs from your chin to the hyoid bone in your throat, and the hyoid has no joint of its own: it is held entirely by muscle and fascia. The deep cervical fascia that wraps the neck also continues up into the jaw and face, so tension under the chin is shared with the front of the neck.
Why does my neck feel tight when my jaw hurts?
The jaw and neck feed into the same nerve processing region in the brainstem. When the jaw is under stress from clenching or misalignment, that message travels the same pathway as neck pain. The brain reads them together, which is why jaw tension so often produces neck tightness, and vice versa.
Why do my TMJ and neck symptoms keep coming back after treatment?
Most treatments address the jaw or the neck in isolation. When the underlying postural pattern organizing both has not changed, the symptoms return. People who have had multiple treatments without lasting relief typically still have an unaddressed jaw-cervical relationship driving the pattern.
Can TMJ cause tension headaches?
Yes. Because the jaw and neck share fascia and a nerve pathway that terminates in the upper cervical spine, jaw dysfunction commonly refers pain to the temples, behind the eyes, and the base of the skull, which is the pattern most people recognize as a tension headache.
Does fixing my posture help TMJ and neck pain?
Often, yes. The jaw and neck sit within a postural chain that runs down through the spine to the feet. When the whole chain is organized better, the load driving the jaw-neck pattern eases, which is why addressing posture tends to hold longer than treating either region on its own.
Does jaw alignment affect the neck?
Yes. When the jaw is out of alignment, the muscles that tie it to the neck shift to compensate, which pulls the neck out of its resting position. Trying to realign the jaw on its own, without addressing the neck and the postural chain below it, is why the change so often fails to hold.
Why do I have jaw pain on one side along with neck tension?
Jaw pain on one side commonly travels into the neck on that same side, because the muscles and fascia connecting the two regions carry the load unevenly. The neck tension is usually the jaw pattern showing up one link down the chain.
What gives lasting relief from a TMJ disorder?
Relief that lasts tends to come from addressing the whole jaw-neck pattern rather than the jaw alone, because the neck and the postural chain below it keep feeding the pattern when they are left untouched.
References
- Silveira, A., Gadotti, I. C., Armijo-Olivo, S., Biasotto-Gonzalez, D. A., & Magee, D. (2015). Jaw dysfunction is associated with neck disability and muscle tenderness in subjects with and without chronic temporomandibular disorders. BioMed Research International. PMC4391655
- Walczyńska-Dragon, K., Baron, S., et al. (2014). Correlation between TMD and cervical spine pain and mobility: is the whole body balance TMJ related? BioMed Research International. PMC4090505
- Pirri, C., Fede, C., et al. (2021). Ultrasound imaging of head/neck muscles and their fasciae: an observational study. Frontiers in Rehabilitation Sciences. PMID 36188862
- Oleksy, Ł., Kielnar, R., et al. (2021). Impact of cervical spine rehabilitation on temporomandibular joint functioning in patients with idiopathic neck pain. BioMed Research International. PMC8516540
- De-la-Llave-Rincón, A. I., Alonso-Blanco, C., et al. (2012). Myofascial trigger points in the masticatory muscles in patients with and without chronic mechanical neck pain. Journal of Manipulative and Physiological Therapeutics. PMID 23206962
- von Piekartz, H., Pudelko, A., et al. (2016). Do subjects with acute/subacute temporomandibular disorder have associated cervical impairments: a cross-sectional study. Manual Therapy. PMID 27744136